Monday, July 9, 2012

ECG Interpretation Review #48 (Chest Pain - STEMI - 1st Degree - 2nd Degree AV Block - Infero-lateral - 2-to-1 - Wraparound)

The 12-lead ECG shown in Figure 1 was obtained from 50-year-old woman with “chest tightness”.
  • What two major conclusions should be reached regarding ECG interpretation of this tracing? 
Figure 1 – 12-lead ECG from a 50-year-old woman with chest tightness. (Reproduced from ECG-2014-ePub). – NOTE – Enlarge by clicking on Figures – Right-Click to open in a separate window.
INTERPRETATION: The two conclusions to be reached are: i) that there is a large acute evolving STEMI (ST-Elevation-Myocardial Infarction) in progress; and ii) there is 2nd degree AV block. It may be easiest to first interpret the changes of acute MI:
  • The QRS complex is narrow.
  • The axis is normal.
  • There is no chamber enlargement.
  • Q Waves/R Wave Progression: Q waves are present in each of the inferior leads (II,III,aVF). After a small (but definitely present) initial r wave in lead V1 – there is loss-of-R-wave – with a probable QS in V2 and a definite QS (with notch in downslope of S wave) by lead V3. Abnormal Q waves persist in leads V4-thru-V6.
  • ST-T Wave Changes: There is marked ST elevation in each of the inferior leads. In addition – there is ST segment coving and elevation that appears to begin in lead V2, and persist through to lead V6. T wave inversion (sometimes marked) is seen in each of the leads with ST elevation.
  • Reciprocal Changes – are seen in leads I and aVL. These reciprocal changes entail not only ST depression in lead aVL – but also T wave peaking (which is the “mirror-image” of the deep inferior symmetric T wave inversion).
-------------------------------------------------------
WHAT IS THE RHYTHM in FIGURE 1?
An extra P wave appears to be hiding in the tail portion of each QRS complex on this tracing (Figure 2). This extra P wave is most evident in lead II (RED arrows in Figure 2) – but it is also seen in other leads (BLUE arrows).
  • The underlying atrial rhythm is rapid (~140/minute) and regular.
  • The PR interval preceding each QRS complex is fixed (albeit prolonged to 0.26 second). Thus, every-other-P-wave is conducting – and the rhythm is 2nd degree AV block with 2:1 AV conduction.
Figure 2 – Addition of red and blue arrows to Figure 1 – revealing 2:1 AV conduction in the underlying rhythm (See text).
-------------------------------------------------------
IMPRESSION:  The ECG in Figure 1 suggests a large acutely evolving STEMI involving inferior, anterior and lateral precordial lead areas. Large Q waves have already developed in anterior leads (loss or r between V1-to-V2 – and QS in V2,V3). ST segment coving and elevation persists in these anterior lead areas – though ST elevation is not as marked as it is in inferior leads.
  • Whether the extensive pattern of injury seen indicates acute occlusion of a large dominant circumflex artery vs an LAD (Left Anterior Descending) artery with “wraparound” (an LAD that also supplies the inferior wall) vs some combination of lesions (perhaps with collateralization affecting distribution) – is uncertain. What is certain – is that an extremely large infarction with AV block is acutely evolving.
We define the type of AV conduction disturbance seen in Figures 1,2 as 2nd degree AV block with 2:1 AV conduction:
  • In theory – the conduction disturbance could be either Mobitz I (AV Wenckebach) or Mobitz II AV block. The reason we cannot absolutely distinguish between these two possibilities is that one never sees two beats conducted in a row (so that we can’t tell IF the PR interval would lengthen if it did have an opportunity to do so).
  • That said – we strongly suspect the conduction disturbance represents 2nd degree AV block, Mobitz Type I (Wenckebach) – because: i) Mobitz I is far more common than Mobitz II – especially in the setting of acute inferior MI when there is also 1st degree AV block for conducting beats; and  ii) the QRS complex is narrow (as it almost always is with Mobitz I – vs QRS widening that is usually seen with Mobitz II).
  • PEARL: It would be easy to overlook 2:1 AV block in this tracing. Awareness that various forms of AV Wenckebach commonly occur with acute inferior MI should increase your index of suspicion that this conduction disturbance may be “in hiding” whenever ST segment elevation is marked – and you either see: i) a pattern of grouped beating; or ii) a longer-than-expected PR interval preceding those beats that are conducting (as seen here). Use of calipers may prove invaluable for confirming your suspicion.
BOTTOM LINE: Acute reperfusion is urgently needed for this patient.
---------------------------------------------------- 

NOTE: - Relevant PDFs on ECG features in this case
---------------------------------------------------- 

Thursday, July 5, 2012

ECG Interpretation Review #47 (Normal Variants - Early Repolarization - Benign - ST Elevation - Pericarditis - ERP - STEMI)

The 12-lead ECG shown in Figure 1 was obtained from 50-year-old man with chest discomfort.
  • Is this ECG likely to reflect acute anterior STEMI? – acute pericarditis? – or ERP (Early Repolarization Pattern) without acute process?

Figure 1 – 12-lead ECG from a 50-year-old man with chest discomfort.


INTERPRETATION: Using our systematic sequential approach (rate-rhythm-intervals-axis-hypertrophy-QRST changes) – We interpret the 12-lead ECG in Figure 1 as follows:
  • The QRS complex is narrow.
  • There is slight but definite variability in the R-R interval throughout the tracing. The rhythm is sinus arrhythmia.
  • All intervals (PR,QRS,QT) are normal; the axis is normal (approximately +70 degrees).
  • There is voltage for LVH (deepest S in V1,2 + tallest R in V5,6 ≥35). No other sign of chamber enlargement.
  • Q-R-S-T Changes: There are small q waves in the inferior and lateral precordial leads.  R wave progression is normal (ie, transition occurs between leads V3-to-V4 ).  T waves are peaked.  There is some J-point ST segment elevation (with upward concavity = "smiley" configuration) in multiple leads - and there is shallow symmetric T wave inversion in lead aVL.
-------------------------------------------------------
IMPRESSION: There is some baseline artifact (seen most in leads I, II, III, aVL . . . - albeit not enough to impede our interpretation). Sinus arrhythmia. Voltage for LVH. Shallow T wave inversion in lead aVL – plus – 1-2mm of J-point ST segment elevation with upward concavity in a number of leads … STOP! ...
  • Interpretation of the ECG in Figure 1 beyond the “STOP” depends greatly on the clinical setting.
  • IF this ECG was obtained from an otherwise healthy young adult without cardiac symptoms – we would interpret the isolated shallow T inversion in lead aVL as normal given the relatively vertical QRS axis and predominantly negative QRS complex in this lead (See Figure 2 below).
  • Similarly – We would interpret the slight (but real) upward concavity (“smiley”) precordial ST elevation as consistent with ERP (See Figure 3 below).

HOWEVER – The situation in this case is different – because the patient whose ECG is shown in Figure 1 is 50 years old and IS having chest discomfort ...
  • Consideration therefore HAS to be given to the possibility that the precordial lead ST elevation seen could represent an early stage of acute anterior STEMI (ST Elevation Myocardial Infarction) – especially given the T wave inversion in lead aVL.
----------------------------------------------------
NOTE: We complete our interpretation of this case (and the ECG in Figure 1) at the bottom of this Blog post. Before doing so – we address a number of key concepts relating to clinical assessment of anterior lead ST elevation.
----------------------------------------------------

Normal T Wave Inversion:
Five leads (III,aVF,aVL,aVR,V1) – may normally display moderate-to-large Q waves and/or T wave inversion in otherwise healthy adults. Thinking of a “reverse Z” (à la Zorro) may help recall which leads these are (Figure 2):
  • While we cannot rule out the possibility that the shallow T wave inversion in lead aVL of Figure 1 reflects ischemia – this T inversion is much more likely to be normal in this patient because: i) T wave inversion is isolated (it is only seen in lead aVL); ii) T inversion is shallow; iii) the QRS complex in aVL is predominantly negative in this patient with a relatively vertical QRS axis (conditions that predispose to the normal finding of some T inversion in aVL); and iv) no acute change is seen in other limb leads.

Figure 2 – Schematic tracing showing those leads that may normally manifest even large Q waves or deep T wave inversion (leads III,aVF,aVL,aVR,V1). Thinking of a “reverse Z” may facilitate recall.


----------------------------------------------------
ST Segment SHAPE:
The shape of ST elevation is more important than the amount of elevation (Figure 3). Acute MI may occur with only minimal ST elevation:
  • ST elevation with an upward concavity (ie, “smiley” configuration) is usually benign – especially when seen in an otherwise healthy, asymptomatic individual (especially when seen with notching or slurring of the J point in one or more leads). This ST segment variant is known as ERP (Early Repolarization Pattern).
  • In contrast – ST elevation with coving or a downward convexity (“frowny” ) – is much more likely to be due to acute injury (from ischemia/MI).
  • KEY POINT: History is ever important. Although ST elevation with a “smiley” configuration and J-point notching often reflects a normal variant – this is only true IF the patient is asymptomatic. An identical ST-T wave pattern from a patient with chest pain must be assumed acute until proven otherwise.
  • IF in doubt – Admit the patient! Look at old tracings to compare. Repeat the ECG.

Figure 3 – Schematic showing upward concavity (“smiley” ) ST elevation that is usually benign – especially when J-point notching is seen in one or more leads. In contrast – ST segment coving (“frowny” ) – is much more likely to be due to acute injury/infarction.


----------------------------------------------------
Are ST Segments Truly Elevated in Figure 1? 
ST segment elevation in Figure 1 is subtle but real (Figure 4):
  • We judge ST segment deviations with respect to the PR segment baseline. In Figure 4 – the blowup of leads V1,V2 shows the J-point to be clearly elevated above the PR segment baseline. We estimate 1-2mm of upward concavity ST elevation in lead V2 (although we admit that subtle rounding of the J-point area in this lead makes precise determination of the amount of ST elevation difficult).

Figure 4 – Second look at the ECG shown in Figure 1 from this 50 year-old man with chest discomfort. Blowup of leads V1,V2 illustrates subtle but real upward concavity ST elevation above the PR segment baseline (See text).


----------------------------------------------------
Putting It All Together:
As stated earlier – the ECG in Figure 1 shows sinus arrhythmia; voltage for LVH; shallow T wave inversion in lead aVL – plus – 1-2mm of J-point ST segment elevation with upward concavity in a number of leads … Our impression is probable ERP (and not anterior STEMI or pericarditis) because:
  • ST elevation manifests and upward concavity (“smiley” ) configuration (albeit no J-point notching is seen).
  • ST elevation is seen (at least in small amount) in all precordial leads. IF acute anterior STEMI was evolving – one would expect additional ST-T wave abnormality elsewhere on this tracing given the extent of ST elevation.
  • The shallow T wave inversion in lead aVL is isolated and probably normal given the patient’s relatively vertical QRS axis and predominantly negative QRS in lead aVL.
  • The q waves seen on this tracing are small and narrow. They most probably are normal septal q waves (which are typically seen in lateral leads and sometimes also in inferior leads in patients with a vertical axis).
  • The ECG picture in Figure 1 is not suggestive of acute pericarditis (it lacks sinus tachycardia; ST elevation is absent in the limb leads; there is no PR depression).

We conclude our interpretation of the ECG in Figure 1 with the statement: “Urge clinical correlation”. The point to emphasize is that although we would be relatively comfortable that the ECG shown in Figure 1 is unlikely to represent early acute anterior STEMI – We can not rule out this possibility on the basis of this single tracing! How to proceed with only a ~90% comfort level that the ECG in Figure 1 is benign would depend:
  • IF this patient presented to the office with a history of chest discomfort that was relatively unconvincing for ischemic pain – we would probably manage the case on an ambulatory basis. We would be that much more inclined to do so IF history and physical exam suggested a non-cardiac cause (peptic ulcer disease; musculoskeletal chest pain, etc.).
  • Access to a prior ECG on this patient might prove invaluable (especially if it confirmed baseline anterior ST elevation and T wave inversion in aVL of similar nature to that seen in Figure 1).
  • On the other hand – IF this 50-year-old man presented to the ED (Emergency Department) with new-onset chest discomfort (and no prior tracing available) – he would almost certainly be admitted to the hospital. One simply can’t rule out the possibility of early anterior STEMI on the basis of this single tracing… (In our experience – such patients with new-onset chest discomfort are not sent home from the ED).


----------------------------------------------------
Should the Cath Lab Be Activated?
Taking the 2nd scenario presented above (ie, that this 50-year-old man presented to the ED with the ECG in Figure 1 and a history of new-onset chest discomfort) – the question arises as to whether the cath lab should be activated for possible acute reperfusion on the basis of this tracing? IF Figure 1 in fact represents an early stage of anterior STEMI – then prompt reperfusion becomes a critical determinant of optimal prognosis.
  • At what point to activate the cath lab is difficult to say from the comfort of our home computer as we view this tracing …. Sometimes – “Ya just gotta be there …”. That said – We most probably would not activate the cath lab on the basis of what we see in Figure 1.
  • Access to a prior ECG on this patient might be revealing (if a prior tracing can be found…).
  • Repeating the ECG in short order may establish the diagnosis. With acute evolving infarction – significant change may be evident on ECG in as little as 20-to-30 minutes.
  • Obtaining an Echo at the bedside in the ED while the patient is having chest discomfort may provide invaluable assistance in determining the likelihood of an acute event. If an anterior wall motion abnormality is seen during symptoms — this becomes highly suggestive of an acute event. On the other hand, if during chest discomfort the Echo is entirely normal — this makes an acute event much less likely. (NOTE: We emphasize 2 points regarding ED use of Echo for this purpose: i) these Echos may be challenging to read, so expertise is needed to KNOW whether wall motion abnormality is or is not present; and ii) an Echo is only helpful IF obtained during chest discomfort. If chest discomfort has resolved and the Echo is normal — unfortunately nothing can be ruled out!)
  • STAT troponin values may confirm acute infarction (though even high-sensitivity troponins would not rule this possibility out if they were normal).
  • IF still in doubt after reexamining the patient and the above series of steps – Consider consulting the Cardiologist-On-Call to assist in the decision-making process. There are times when acute cath may be performed even without definitive diagnosis – although in this case, careful observation with close serial follow-up will almost certainly tell the tale over the next few hours. But at least the cardiologist is aware in the event a surprise occurs and the ECG evolves ...

----------------------------------------------------
FINAL Thoughts: Is there Help in the Literature?
Smith et al have developed a multivariate equation to assist in acute evaluation of the patient with anterior ST elevation (Ann Emerg Med 60:45, 2012). Findings from their retrospective analysis of a large data set are insightful in this case – and further support our suspicion that the ECG in Figure 1 is most probably benign. These include relatively taller R wave amplitude and a QT interval that is not prolonged in Figure 1. That said – overlap exists in the parameters used in the calculated Smith equation, such that we are still left with being unable to exclude an acute process on the basis of the number score reported.  – END OF CASE –
----------------------------------------------------


Please click on the icon below for a pdf Link to Section 09.0 (from our ECG-2014-ePub) on assessment of ST-T waves. The part on Early Repolarization begins in Section 09.14 in this pdf:


----------------------------------------------------

Friday, June 22, 2012

ECG Blog #46 — STEMI or a Broken Heart?


The ECG shown was obtained from a 74-year-old woman who presented with abrupt onset of severe renal colic but no chest pain. Based on findings seen in her ECG — acute cardiac catheterization was performed. Her coronary arteries were normal on cath. Troponins were only minimally elevated. 
  • How would you interpret her ECG? 
  • How might you explain the finding of normal coronary arteries on cardiac catheterization?

Figure 1: ECG obtained from a 74-year old woman with renal colic, but no chest pain.


INTERPRETATION: The ECG shows sinus rhythm at a rate close to 100/minute. The PR and QRS intervals appear to be normal — but the QT is prolonged. The axis is normal (approximately +70 degrees). There is no chamber enlargement. An rSr’ complex is noted in lead V1. 
  • Assessment of Q-R-S-T Changes is remarkable for the presence of inferior Q waves — normal transition (R wave becoming taller than the S wave between leads V3-to-V4) — and ST segment coving with marked elevation in the inferior leads. This is accompanied by deep T wave inversion. 
  • Similar abnormal ST segment coving and elevation (albeit not as marked) is also present in leads V4,V5. Deep, symmetric T wave inversion that begins in lead V3 is seen in V4,V5. 

Despite the absence of chest pain — the impression from interpretation of this ECG was “probable acute STEMI" (ST-Elevation Myocardial Infarction) with need for immediate cardiac catheterization and probable reperfusion”. Surprisingly, cardiac catheterization revealed normal coronary arteries. Instead — the ventriculogram revealed apical ballooning with hypercontractility of the cardiac base characteristic of Takotsubo Cardiomyopathy. The patient was treated supportively with recovery of left ventricular function over the next few weeks. 
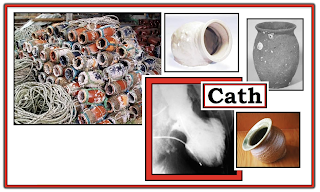
  • Takotsubo Cardiomyopathy is an underappreciated cause of acute ECG abnormalities and new-onset heart failure. The entity was first described in Japan in 1990, with the name takotsubo being derived from a specially designed container used by Japanese fishermen to trap octopuses. The unusual round bottom and narrow neck design of takotsubo resembles the diagnostic picture on cardiac catheterization obtained as a result of ballooning of the cardiac apex with hypercontraction of the base (Figure-2).
  • Other names attributed to this entity include “stress cardiomyopathy” and “broken-heart syndrome” — in reference to the common occurrence of severe physical or emotional stress prior to onset of the disorder. Awareness of this syndrome is important — because the initial ECG may mimic a large apical infarction (with inferior and anterior ST segment elevation). Transient heart failure is common during the initial stages, but fortunately resolves within a few weeks in most cases.

Figure-2: Collection of actual takotsubo showing the round bottom and narrow neck — that resembles the diagnostic picture seen on the cardiac catheterization ventriculogram (shown here during end-systole). Note characteristic "ballooning of the apex and hypercontractility of the base during cardiac cath (See text).

The Mechanism of Takotsubo CMP (CardioMyoPathy):

The precise mechanism for Takotsubo CMP remains elusive. While factors such as coronary spasm; disturbance of the microcirculation; coronary artery anatomic variation; and neurogenic myocardial stunning have all been implicated — their role is uncertain. What has been shown — is that abnormal response to an increase in endogenous catecholamines is almost always involved. Blood epinephrine and norepinephrine levels are unmistakably elevated (sometimes dramatically) in patients with Takotsubo CMP.

  • In addition — there is more-than-coincidental preceding occurrence of intense situational or psychological stress in many patients. This may be in the form of severe emotional stress (death of a loved one; break-up from significant other; overwhelming anxiety/depression) — pain — and/or fear (from earthquake or other catastrohic event). It is easy to understand the rationale for other names that have been used for this syndrome (ie, "Stress" Cardiomyopathy or "Broken-Heart" Syndrome).
  • Although consensus is still lacking regarding specific criteria for defining Takotsubo CMP — there is general agreement that cardiac cath is diagnostic (ie, apical ballooning but no "culprit" artery).


SUMMARY of the Clinical Picture:

Takotsubo CMP is most typically seen in an older patient (most often in a post-menopausal woman) — who presents with chest pain or new heart failure. Look for the following features:

  • Likelihood of preceding severe physical/emotional stress.
  • Markedly abnormal initial ECG — often with diffuse ST elevation in inferior and antero-lateral leads (apical or LAD "wraparound" distribution). Associated T wave inversion and/or Q waves (sometimes deep) may be seen. Acute extensive STEMI-in-evolution is frequently the initial diagnosis (as it was in today's case).
  • Usually no more than modest troponin elevation (troponins are often elevated — but generally not nearly as high as expected given how marked ECG changes are).
  • Transient LV dysfunction — which may be severe initially (some patients present in pulmonary edema/cardiogenic shock requiring intra-aortic balloon pump support). LV function usually resolves within a few weeks.
  • Possibility of potentially life-threatening arrhythmias during the acute phase (including VT/Torsades de Pointes).
  • Absence of pheochromocytoma, myocarditis or other underlying cardiac pathology to explain findings.
  • Generally favorable prognosis (often with full recovery within 1 month) — but fatalities have been reported (from LV free wall rupture; intractable pulmonary edema).


NOTE: Variations on the above theme do exist. The syndrome of Takotsubo CMP is not limited to post-menopausal women — the ECG does not always show marked abnormality — and severe stress does not uniformly precede presentation.

  • Anatomic areas other than the apex may also be affected. For example — there may be an “inverted takotsubo” form, in which the apex is spared but the base of the heart is hypokinetic. The existence of such Takotsubo variants helps to explain the likely multifactorial etiology to this interesting syndrome.


PEARL: Think of the possibility of Takotsubo CMP when confronted with a patient who presents with a markedly abnormal ECG that doesn’t quite “fit” the clinical picture. 

  • ECG findings may be out of proportion to clinical findings. ECG changes may involve several lead areas (especially inferior and anterior precordial leads — which typically assess the cardiac apex).
  • There may be an element of heart failure. Serum troponins may be positive.
  • The patient is usually an older adult (especially a post-menopausal woman).
  • There has usually been some form of severe preceding “stress”.


============================

ADDENDUM (1/2/2022):

I find it easy to forget about Takotsubo Cardiomyopathy. I've observed that many clinicians have a tendency to overlook this disorder. In the hope of serving as a helpful reminder — I've summarized in Figure-3 below, the ECG Findings that might be expected in Takotsubo Cardiomyopathy (adapted from Namgung in Clin Med Insights Cardiol). 


Figure-3: ECG Findings in Takotsubo Cardiomyopathy (adapted from Namgung in Clin Med Insights Cardiol).


============================
Related Material:
  • For another case of Takotsubo Cardiomyopathy — Please see the March 25, 2020 post in Dr. Smith's ECG Blog. Please check out My Comment at the bottom of the page!


Monday, June 11, 2012

ECG Blog #45 — Muscular Dystrophy?

The ECG shown was obtained from a 22-year-old man in a wheelchair. 
  • How would you interpret the tracing? 
  • Can you think of a clinical entity that might account for this clinical scenario? 

Figure-1 - 12-lead ECG obtained from a 22-year-old man in a wheelchair. What clinical entity is suggested? 


INTERPRETATION: The ECG shows sinus rhythm at about 70/minute. The PR interval is normal – but the QRS is prolonged to at least 0.12 second. QRS morphology in the 3 key leads (I,V1,V6) is not consistent with either left or right bundle branch block. Therefore — we would classify the conduction defect as nonspecific IVCD (IntraVentricular Conduction Delay). 
  • Continuing with the interpretation — We note marked LAD (left axis deviation) consistent with LAHB (Left Anterior HemiBlock). QRS amplitude is markedly increased in lead aVL — although reliability of the ECG diagnosis of LVH (left ventricular hypertrophy) is reduced in the presence of conduction defects.
  • Regarding Q-R-S-T Changes — there are deep and wide Q waves in the high lateral leads (I,aVL). In addition — there is a small q wave in lead V2. 
  • QRS morphology in lead V1 is peculiar, as there is an rSr’s’ complex. 
  • This is followed by abrupt transition by lead V2, in which a disproportionately tall R wave is noted. 
  • R wave amplitude drops off by lead V3 — with persistent S waves seen throughout the remaining precordial leads. 
  • There is ST segment depression in lateral leads I and aVL which may reflect ‘strain’ from suspected LVH. That said — ST-T wave changes do not appear to be acute. 
=======================

IMPRESSION: This ECG is clearly abnormal and highly unusual for a young adult. Given the history of a “22-year-old man in a wheelchair” should suggest the possibility of a cardiomyopathy such as Duchenne Muscular Dystrophy (DMD). There are over 20 different genetic forms of muscular dystrophy — of which DMD is the most common of these rare disorders. DMD is almost exclusively seen in males, with unfortunate outcome of progressive muscle deterioration and weakness that invariably leads to death at an early age.
  • Cardiac involvement is the rule with most muscular dystrophies. The most common ECG abnormalities in DMD (and in other muscular dystrophies) include the following: i) QRS widening from conduction defects (usually nonspecific IVCD); ii) Abnormal Q waves not due to infarction (especially in lateral leads); and, iii) A polyphasic rSr’s’ in lead V1 — often with surprisingly tall anterior precordial R waves. All of these features are seen in Figure-1 !

  • Please Click on Figure-2 below for brief review of clinical and ECG features of Duchenne, Becker, and other muscular dystrophies.

Figure-2 - Clinical and ECG features of Muscular Dystrophy.


=======================
ACKNOWLEDGMENT: My appreciation goes to Dr. Harsha Nagarajarao (of Cardiology Boards) for allowing me to use this tracing.
=======================