Tuesday, May 10, 2011

ECG Interpretation Review #21 (Complete AV Block vs AV Dissociation)

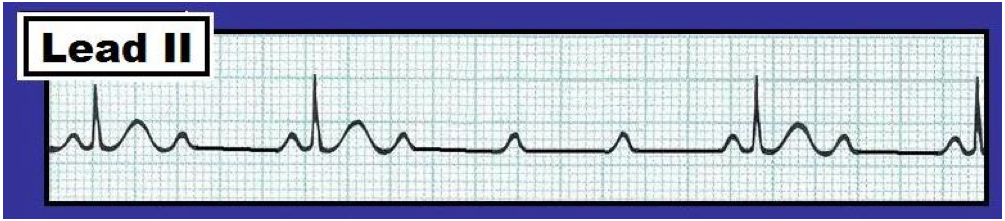
The lead II rhythm strip shown below in Figure 1 was obtained from an asymptomatic middle-aged adult. Is there complete (3rd degree) AV Block?  How would you proceed clinically?
Figure 1 - Lead II rhythm strip from an asymptomatic adult.
Is there 3rd degree AV block?
(Figure reproduced from ACLS-2013-ePub ).
- Note - Enlarge by clicking on Figures - Right-Click to open in a separate window.
INTERPRETATION:  The ventricular rhythm in the Figure is regular at a rate just over 50/minute (since the R-R interval is slightly less than 6 large boxes in duration).  The QRS complex is narrow, indicating a supraventricular etiology.  P waves are present – however, they are not consistently conducting.  Instead, the PR interval is changing. The PR interval preceding beats #3 and 4 (arrows) is clearly too short to conduct.
------------------------------------------------------
In ECG Blog #19 – we defined the 3 degrees of AV block as follows:
  • 1st degree AV block – in which all atrial impulses are conducted to the ventricles, albeit with delay (so that the PR interval exceeds 0.20 second).
  • 2nd degree AV block – in which some (but not all) atrial impulses are conducted to the ventricles.
  • 3rd degree (or “complete”) AV block – in which none of the atrial impulses are conducted to the ventricles, despite having adequate opportunity for conduction to occur.
The key to the diagnosis of complete AV block is in the last part of the definition: No atrial impulses are conducted to the ventricles “despite having adequate opportunity for conduction to occur”. Although beats #3 and 4 in Figure 1 (and possibly also beat #2) are not conducted to the ventricles – none of these beats has a “chance” to conduct, since the PR interval is simply too short. Thus, we have no idea if any degree of AV block is present – since we cannot tell from Figure 1 if P waves could conduct were they given the opportunity to do so. We therefore interpret this tracing as showing “AV dissociation” – since at least some P waves are unrelated to the QRS complexes that follow them. The term AV dissociation should never be used as a “diagnosis” per se.  Instead – it is the result of the underlying rhythm on the tracing.  In this case – the underlying rhythm is sinus bradycardia at a rate of 50/minute (the P-P interval is precisely 6 large boxes in duration for each of the P waves on this tracing). AV dissociation occurs by “default”.  That is – due to the relatively slow sinus rate, a nodal rhythm (at ~52/minute) takes over. This rhythm variant is not uncommonly seen in otherwise healthy young adult individuals. It may well be that there is no degree of AV block present, and that normal conduction will resume whenever the sinus node speeds up to a normal rate.
--------------------------------------------------
Distinction Beween AV Dissociation and Complete AV Block:  In contrast to Figure 1 – the lead II rhythm shown in Figure 2 illustrates complete (3rd degree) AV block.  
Figure 2 - Lead II rhythm strip showing 3rd degree AV block.
(Figure reproduced from ACLS-2013-ePub - pg 101)
- Note - Enlarge by clicking on Figures - Right-Click to open in a separate window.
The atrial and ventricular rates in Figure 2 are both regular with no relation between P waves and neighboring QRS complexes. The QRS complex is wide, indicating AV block at the ventricular level.  But the main distinction between Figures 1 and 2 is that despite more than adequate opportunity to conduct – none of the P waves in Figure 2 are conducted. We would not expect the P wave hidden in the T wave of beat #3 to conduct (because it occurs in the ST segment and is probably in the absolute refractory period). Similarly – the P wave preceding beat #1 in Figure 2 might not conduct (because this PR interval is not overly long). But virtually all other P waves on this tracing occur at a place when there should have been more than ample opportunity for conduction to occur. The diagnosis of complete AV block is therefore established.
--------------------------------------------

  - See also ECG Blog Reviews #19, 20 – and Section 20.0 of our ACLS-2013-ePub -
-------------------------------------------- 

Monday, May 9, 2011

ECG Interpretation Review #20 (High-Grade AV Block - Mobitz I vs Mobitz II?)

The Lead II rhythm strip shown below in Figure 1 was obtained was obtained from a patient during cardiopulmonary resuscitation. It is a follow-up tracing to our ECG Blog Review #19. The patient was hypotensive at the time Figure 1 was recorded. Does the rhythm represent 2nd degree AV Block, Mobitz Type II? How to proceed clinically?

Figure 1 - Lead II rhythm strip from a patient in cardiac arrest.
Is this 2nd degree AV block, Mobitz Type II?


INTERPRETATION:  The ventricular rhythm in Figure 1 is slow and irregular. Nevertheless – the QRS complex is narrow, and the atrial rate is regular at ~115/minute. The P waves immediately preceding each QRS complex manifest a fixed (and normal) PR interval. Thus, these P waves are conducting. This means that the rhythm is not complete AV block.  Since there are many non-conducted P waves on the tracing – the rhythm must represent some form of high-grade 2nd degree AV block.
-----------------------------------------------------

As discussed in ECG Blog Review #19 – Second degree AV blocks are generally classified into one of 3 types:
  • Mobitz I (AV Wenckebach) – in which the PR interval progressively lengthens until a beat is dropped.  This is by far the most common form of 2nd degree AV block. 
  • Mobitz II – in which there is a constant PR interval for consecutively conducted beats until one or more beats are dropped.
  • 2-to-1 AV Block – in which every-other-P-wave is conducted. Because one never sees two consecutively conducted beats – you can not tell if the PR interval is lengthening or not.  As a result – it is impossible to know for sure whether this form of 2nd degree AV block represents Mobitz I or Mobitz II.

-----------------------------------------------------
Returning to this Case: There are features of both Mobitz I (AV Wenckebach) and Mobitz II on the tracing shown in Figure 1. In favor of Mobitz II is the low conduction ratio and high grade of AV block. No less than 3 P waves in a row are non-conducted in the middle of the tracing.  However, the QRS complex is narrow – which is highly unusual for Mobitz II.
  • Clinically – the importance of distinguishing AV Wenckebach (Mobitz I) from Mobitz II relates to the much better prognosis of Mobitz I, a generally better response to treatment with Atropine, and a much lower likelihood of needing a pacemaker. That said – it is impossible to be certain which form of 2nd degree AV block is present from the tracing in Figure 1 alone, since one never sees two P waves in a row that conduct.  Thus, one can not tell if the PR interval is progressively increasing until the point of non-conduction.  Although unusual for Mobitz I – more than one P wave in a row may be blocked on occasion with this conduction disturbance.  From a practical treatment perspective, however – distinguishing between Mobitz I and Mobitz II appears to be less important since a pacemaker may be needed in either case unless the high-grade degree of AV block improves.

-----------------------------------------------------
FINAL (Advanced) PEARL: Even though far fewer P waves are conducted in Figure 1 from this Blog post (above) compared to the rhythm strip showing 2-to-1 AV conduction in Figure 1 from ECG Blog Review #19 (We reproduce that 2:1 AV block tracing below) – the “degree” of AV block per se has not necessarily “worsened”. Why not?  HINT: Has the atrial rate changed in the two tracings?

Figure 1 from ECG Blog Review #19 - Lead II rhythm strip showing 2:1 AV block.


ANSWER: The atrial rate in Figure 1 of this Blog post (at the top of this page) is now faster (~115/minute) than it was when there was 2:1 AV conduction (Note the P-P interval in Figure 1 from Blog Review #19 = 3 large boxes = an atrial rate of 100/minute). Rather than “worsening” of the degree of AV block per se – the lower conduction rate may simply be the result of the faster atrial rate.  Treatment of 2nd degree AV block with atropine may at times be a double-edged sword. It may improve the situation (by facilitating conduction through the AV node) – but it can at times worsen the situation by increasing the atrial rate by an amount that may be too fast to conduct. Bottom Line: We suspect that Figure 1 in this Blog post (at the top of this page) represents high-grade 2nd degree AV block, Mobitz Type I – because the QRS is narrow, and Mobitz I is by far the most common form of 2nd degree AV block. Even though treatment with atropine was appropriate (since this drug is often effective for Mobitz I) – atropine paradoxically worsened the situation in this case, because it further increased the atrial rate. Temporary pacing is indicated given bradycardia with hypotension.

------------------------------


  - See also ECG Blog #19 - and Section 20.0 in our ACLS-2013-ePub -
------------------------------

Sunday, May 8, 2011

ECG Interpretation Review #19 (2-to-1 AV Block - Mobitz I vs Mobitz II?)

The Lead II rhythm strip shown below was obtained from a patient during cardiopulmonary resuscitation. Systolic BP was 90 mmHg at the time this tracing was recorded.  Does this represent 2nd degree AV Block, Mobitz Type II?  How to proceed clinically?

Figure 1 - Lead II rhythm strip from a patient in cardiac arrest.
Is this 2nd degree AV block, Mobitz Type II?


INTERPRETATION:  The rhythm in the Figure 1 is slow but regular. The QRS complex is narrow, and a regular atrial rate is seen at 100/minute (arrows). Every other P wave conducts (as evidenced by the fact that a P wave does precede each QRS complex with a fixed PR interval! ).  Traditionally – the AV blocks are divided into 3 degrees based on severity of the conduction disturbance:
  • 1st degree AV block – in which all atrial impulses are conducted to the ventricles, albeit with delay (so that the PR interval exceeds 0.20 second).
  • 2nd degree AV block – in which some (but not all) atrial impulses are conducted to the ventricles.
  • 3rd degree (or “complete”) AV block – in which none of the atrial impulses are conducted to the ventricles, despite having more than adequate opportunity for conduction to occur.
====================================
Second degree AV blocks are further classified into 3 types (Figure 2):

Figure 2 - Types of 2nd Degree AV Block:
A) Mobitz I (AV Wenckebach); B) Mobitz II; and C) 2-to-1 AV Block.

  • Panel A = Mobitz I (AV Wenckebach) – in which the PR interval progressively lengthens until a beat is dropped.  This is by far the most common form of 2nd degree AV block. Mobitz I usually occurs at the level of the AV node.  As a result – the QRS complex is typically narrow. Mobitz I is generally associated with inferior infarction; it often spontaneously resolves, and typically responds to atropine (which works on the AV node).
  • Panel B = Mobitz II – in which there is a constant PR interval for consecutively conducted beats until one or more beats are dropped. Because Mobitz II typically occurs low down in the conduction system – the QRS complex is generally wide. This less common form of 2nd degree AV block is generally associated with anterior infarction; it usually does not respond to atropine – and is important to recognize because pacing will probably be needed.
  • Panel C = 2-to-1 AV Block – in which one never sees two consecutively conducted beats, so that you can not tell if the PR interval is lengthening or not.  As a result – it is impossible to know for sure whether this form of 2nd degree AV block represents Mobitz I or Mobitz II.

------------------------------------------------------
Returning to this Case: The rhythm in Figure 1 is the same as the one shown in Panel C of Figure 2. Because two conducted beats never occur in a row - we are unable to be certain of the type of 2nd degree AV block. That said – We strongly suspect this rhythm represents 2nd degree AV block, Mobitz Type I (AV Wenckebach) because: i) Mobitz I is so much more common than Mobitz II; and ii) the QRS complex is narrow, as it almost always is with Mobitz I.  Finding additional rhythm strips on this patient that clearly showed progressive lengthening of consecutively conducted QRS complexes before dropping a beat would strongly support our suspicion.  Clinically the distinction is important because no treatment (other than perhaps atropine) is likely to be needed for Mobitz I (especially given that the ventricular rate in Figure 1 is not overly slow at 50/minute). In contrast – pacing would probably be needed if the rhythm was Mobitz II.

-------------------------------------------------


  – See also this pdf from Section 20.0 of our ACLS-2013-ePub –
-------------------------------------------------

Saturday, March 19, 2011

ECG Blog #18 — aVery Fast Tachycardia ...

QUESTION: The ECG below was obtained from a middle-aged woman with new-onset palpitations. She was otherwise not in distress, did not complain of chest pain, and had a blood pressure of 90/60 mm Hg at the time this tracing was recorded. 
  • Is she in ventricular tachycardia?
  • How might you treat her? (What medications would you not use?)

Figure 1 - Lead II rhythm strip from a middle-aged woman with palpitations. Is she in VT?


INTERPRETATION:  The rhythm is rapid and irregularly irregular.  No atrial activity is seen.  Although the QRS complex is definitely widened, the gross irregularity of the rhythm makes ventricular tachycardia unlikely.  This leaves atrial fibrillation as the probable diagnosis.  That said — the rate of the rhythm at certain points in the tracing is much faster than is usually seen with atrial fibrillation.
  • Under normal conditions with atrial fibrillation — the refractory period of the AV node does not allow more than 150-to-200 impulses/minute to be conducted to the ventricles. At certain points in Figure 1 — the R-R interval is just over one large box in duration (which corresponds to a heart rate of ~250 beats/minute). This is simply too fast for atrial impulses to be transmitted over the normal (AV nodal) conduction pathway. 
CONCLUSION:  Atrial impulses must be bypassing the AV node. The finding of atrial fibrillation at an exceedingly rapid rate (over ~220/minute) should immediately suggest the likelihood of accessory (AP) pathway conduction in a patient with WPW (Wolff-Parkinson-White) Syndrome.
  • Two additional features in favor of the rhythm in Figure 1 being WPW rather than VT are: i) variation in QRS morphology during the WCT (less likely with VT); and ii) very marked change between some R-R intervals on the tracing (some being extremely short with others being significantly longer).

-------------------------------
About ARRHYTHMIAS with WPW:  
WPW is a syndrome in which one or more accessory conduction pathways exist that allow an alternate route for transmission of the electrical impulse from the atria to the ventricles.  It has an approximate incidence of 2 per 1,000 individuals in the general population — just frequent enough that most emergency care providers will encounter patients with WPW-related arrhythmias from time to time.
     Conduction of the sinus impulse in patients with WPW may be via the normal (AV nodal) pathway — down the accessory tract — or it may alternate between the two.  These patients are prone to develop atrial tachyarrhythmias in which a reentry circuit is set up between the normal AV nodal pathway and the accessory tract (Figure 2).

Figure 2: Pathways of conduction of supraventricular tachyarrhythmias with WPW. Panel A represents the usual path with AVRT; Panel B with AFib (See text).


NOTE on Terminology: The older name for reentry SVT rhythms was PSVT (Paroxysmal SupraVentricular Tachycardia). At present, the more accurate and more commonly-used name = AVNRT (AV Nodal Reentry Tachycardia). When the patient has an AP (Accessory Pathway) that participates in the reentry circuit — the reentry tachycardia is then called AVRT (AtrioVentricular Reciprocating Tachycardia). As explained below — depending on the initial direction of the impulse during the reentry tachycardia (ie, going initially down the AP — or going initially down the AV Node) — AVRT will either be orthodromic or antidromic.

The following are the 4 main arrhythmias encountered in patients with WPW:
  • With AVRT — the tachyarrhythmia is almost always orthodromic (down the normal AV nodal-His-Purkinje system and back up the accessory pathway — as in Panel A of Figure 2). Because conduction goes down the normal AV nodal pathway — the QRS complex is narrow during the tachycardia. AVRT is by far the most common tachyarrhythmia observed in patients with WPW.  It is usually well tolerated by the patient.
  • In contrast, with Atrial Fibrillation in WPW — the tachyarrhythmia is almost always antidromic (down the AP, with retrograde conduction back to the atria over the AV nodal pathway — as in Panel B in Figure 2).  Antegrade conduction over the accessory pathway results in QRS widening during the tachycardia. Because of the short refractory period of the AP, there may be 1:1 conduction of atrial impulses during atrial fibrillation, resulting in a ventricular response that at times exceeds 250 beats/minute (Figure 1).  Such rapid rates may not be well tolerated (the ventricles may not be able to adequately contract at this rate) — and as a result the rhythm can deteriorate into ventricular fibrillation.
  • Although less commonly seen than atrial fibrillation — Atrial Flutter may also occur in patients with WPW.  As with atrial fibrillation — antegrade transmission of atrial impulses is almost always down the AP when patients with WPW develop atrial flutter.  As a result — there may be 1:1 AV conduction (so that the ventricular response may be as fast as 250-350/minute).
  • Note: In those rare (~5%) instances in which AVRT is antidromic — the QRS complex will be wide and the AVRT rhythm may be indistinguishable from VT. It may only be after conversion to sinus rhythm that "telltale" delta waves of WPW can be identified. Fortunately — the vast majority (~95%) of AVRT episodes with WPW are orthodromic (with narrow QRS).
TREATMENT: Although verapamil, diltiazem and digoxin are all effective medications for slowing the ventricular response of rapid atrial fibrillation — they are contraindicated when atrial fibrillation occurs in association with WPW.  This is because each of these drugs may accelerate conduction down the AP, and thereby exacerbate the tachyarrhythmia. 
  • Appropriate medications to consider (that slow antegrade conduction down the AP) — include amiodarone, procainamide or ibutilide.  
  • Be aware of the need to cardiovert the patient IF they decompensate.


==================================
ADDENDUM (added to Blog #18 on 2/1/2012): 
Interpret the 12-lead ECG shown in Figure 3, obtained from an older patient with palpitations. HINT: The answer is related to Figure 1 …

Figure 3: 12-lead ECG from an older patient with palpitations. Is this VT?


INTERPRETATION of FIGURE 3: There is a regular monomorphic WCT (Wide-Complex Tachycardia) seen at the exceedingly rapid rate of nearly 300/minute! (as determined by the occurrence of a QRS complex each large box). This is too fast for VT. Although this rhythm could represent ventricular flutter – it turned out to be atrial flutter at a rate of ~300/minute in a patient with WPW.
  • As was the case in Figure 1 — antegrade (forward) conduction down the AP (Accessory Pathway) is seen when atrial fibrillation or flutter occur in a patient with WPW. This leads to WCT rhythms at rates that are faster than should be seen for VT.
  • Although rare — the importance of recognizing very rapid AFib or Flutter with WPW cannot be overstated. This is because treatment with verapamil/diltiazem/digoxin are all contraindicated. Instead — one should use amiodarone/procainamide/ibutilide – with awareness of the need to immediately cardiovert the patient IF hemodynamic decompensation occurs (Further discussion of treatment recommendations in this pdf from Section 12.0 of our ACLS-2013-ePub).
--------------------------------------------------
- See also ECG Blog #36 and Blog #37 -
--------------------------------------------------

Monday, March 14, 2011

ECG Blog #17 — A Patient with a Pacer and CP

QUESTION: The patient is an older woman with a pacemaker who presents to the office with atypical chest discomfort.  A 12-lead ECG and Lead II rhythm strip was obtained (Figure-1).
  • How would you interpret her office ECG and rhythm strip?
  • Does the pacemaker prevent you from interpreting her ECG?
  • Is the pacemaker working?
  • Clinically - Is anything acute likely to be going on?

Figure 1 - ECG from an older woman with a pacemaker and chest discomfort.


INTERPRETATION: This challenging tracing is from a patient with a VVI pacemaker. As such — it senses the Ventricles - paces the Ventricles — and is Inhibited by a spontaneous beat. Operation and function of VVI pacemakers is simpler than that of newer DDD pacemakers that sense and pace both atria and ventricles, and may either be triggered or inhibited by a spontaneous beat. When interpreting a pacemaker tracing - we seek to determine IF the pacemaker is both sensing and pacing appropriately. This will often be extremely difficult to do from the surface ECG with newer DDD models showing atrial and ventricular spikes, especially if the pacing rate varies due to rate-responsiveness functions. VVI pacing (as seen in Figure 1) is the one time you can often feel confident from inspection of the 12-lead ECG alone (without formal interrogation of the device) that the pacemaker is or is not appropriately functioning (Figure 2):

Figure 2 - Labeling of the tracing in Figure 1.


We interpret this tracing by making the following points:
  • Beats #1, 2, and 3 in Figure 2 are paced (each QRS complex for these first 3 beats is preceded by a tiny vertical pacer spike best seen in the lead II rhythm strip). The rate of the pacemaker is ~60/minute (the R-R interval from one pacer spike to the next for these first 3 beats is about 5 large boxes).
  • Beat #4 is a spontaneous beat.  Its QRS complex is narrow and not preceded by a pacer spike.
  • The pacemaker appears to be sensing appropriately because the R-R interval between beats #3-to-4 is shorter than the pacer R-R interval (and therefore the pacer appropriately does not fire).
  • That the pacer is sensing appropriately is confirmed by beat #5 which is again paced, and which is preceded by an R-R interval of 5 large boxes (which is the appropriate amount of time for the pacer to wait before firing).
  • Beats #8, 9, and 10 appear to be spontaneous (they are not preceded by pacer spikes).
  • Beat #7 is probably a fusion beat (since it appears to be preceded by a pacing spike, and manifests a QRS complex intermediate in morphology between paced beats and spontaneous beats).
  • We surmise that the underlying rhythm in this tracing is atrial fibrillation — since we do not see definite P waves in the lead II rhythm strip and the spontaneous beats are irregular (though we acknowledge that baseline artifact makes it difficult to be sure that there truly are no P waves ... ).
  • Finally — a very interesting aspect of this tracing is that the spontaneous beats suggest ischemia!  One cannot say anything about ischemia from paced complexes (ie, from beats #1,2,3,5, or 6).  We cannot be sure about ST-T wave morphology from the fusion beat (beat #7).  However, the T wave of spontaneous beats #4, 8, 9, and 10 in the Lead II Rhythm Strip manifests a worrisome appearance of fairly deep symmetric T wave inversion. Use of time lines (vertical RED lines in Figure 2) show there is corresponding ischemic-looking T wave inversion in leads aVL, V3, and V4 (T wave inversion within the BLUE ovals).

BOTTOM LINE:
  This interesting ECG shows that despite the presence of a pacemaker — it is still possible to assess pacemaker sensing and pacing function, determine the underlying rhythm — and detect ischemic T wave inversion of clinical concern in this older woman with chest discomfort.